Boston Scientific accounts are for healthcare professionals only.

Backed by a Decade of Robust Clinical Evidence
Transcarotid artery revascularization (TCAR) is supported by a comprehensive, contemporary real-world evidence base for carotid revascularization. This well-established evidence base includes over 150,000 patients, more than 530 peer-reviewed publications, and broad adoption across thousands of trained physicians. Pivotal ROADSTER trials, combined with large-scale analyses from sources such as VQI, VISION, and national inpatient datasets, provide a robust and consistent understanding of TCAR performance across diverse patient populations and care settings. Importantly, real-world data captures the vast majority of TCAR procedures and are reinforced by multidisciplinary authorship and strong statistical validation.
Together, this depth and breadth of evidence establish a clear foundation for evaluating TCAR by ENROUTE across four critical dimensions: Safety, Durability, Reproducibility, and Patient Compatibility.
Safety
Dermody, M. (2025). Prospective, Multicenter Evaluation of Transcarotid Artery Revascularization (TCAR) In Standard Risk Patients: 1-Year Outcomes of the ROADSTER 3 Study. Presented at VIVA Conference 2025.
Prospective, Multicenter Evaluation of Transcarotid Artery Revascularization (TCAR) In Standard Risk Patients: 1-Year Outcomes of the ROADSTER 3 Study
First-ever, independently adjudicated, prospective, multicenter trial evaluating real world usage of TCAR using the ENROUTE™ Transcarotid Stent System (TSS) in conjunction with the ENROUTE™ Transcarotid Neuroprotection System (NPS) for the treatment of carotid stenosis in standard surgical risk patients.
Stroke Rates
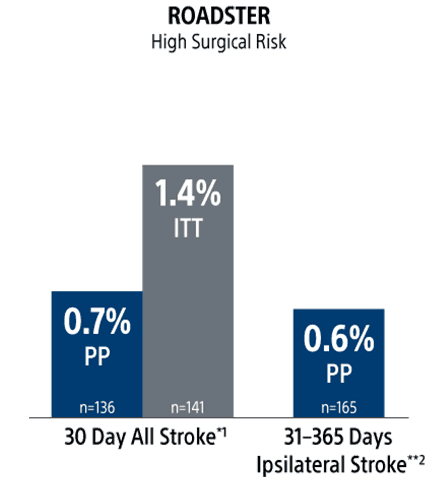
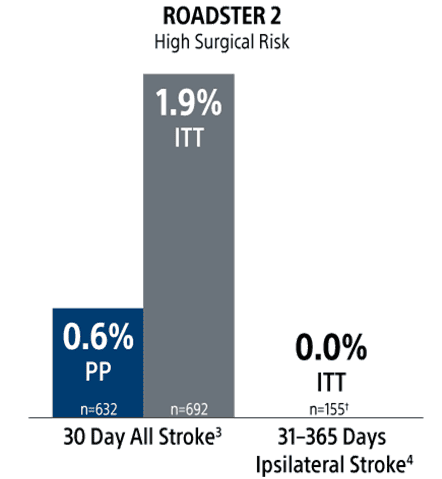
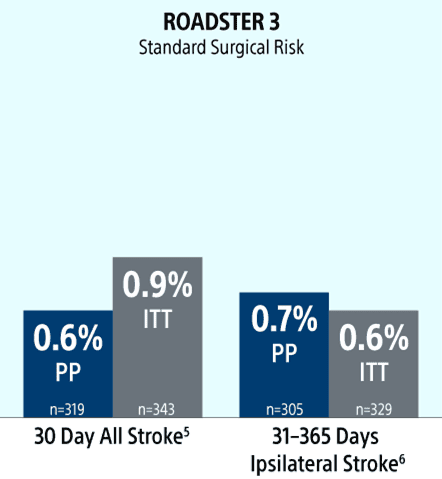
Stroke Rates
ITT = intent to treat
PP = per protocol
September 2021, Journal of Vascular Surgery, Patric Liang
Expansion of Transcarotid Artery Revascularization to Standard Risk Patients for Treatment of Carotid Artery Stenosis
The study provides strong real-world evidence that TCAR can achieve perioperative and 1-year outcomes comparable to carotid endarterectomy in standard-risk patients, supporting broader use of TCAR beyond the high-risk population for whom it was originally approved.
August 2022, Journal of Vascular Surgery, George Q. Zhang, MD, MPH
Transcarotid artery revascularization is associated with similar outcomes to carotid endarterectomy regardless of patient risk status
Using VQI registry data, this study found that TCAR delivered perioperative stroke and death outcomes comparable to CEA in both high-risk and standard-risk patients, while TF-CAS had less favorable results. The findings challenge the utility of current CMS high-risk criteria for determining TCAR eligibility.
November 2023, CNS Operative Neurosurgery, Ian A. Ramsay, BS
Perioperative Outcomes in Transcarotid Artery Revascularization Versus Carotid Endarterectomy or Stenting Nationwide
Using a national inpatient database, this study found that TCAR achieved perioperative stroke and mortality outcomes comparable to carotid endarterectomy while offering a less invasive treatment option. TCAR may be preferred over transfemoral carotid artery stenting in patients who are not candidates for CEA, while also offering a less invasive alternative for patients who are eligible for CEA.
January 2026, Journal of Vascular Surgery, Elisa Caron, MD
Comparative outcomes of transfemoral carotid artery stenting versus carotid endarterectomy versus transcarotid artery revascularization in standard- and high-risk patients since the CMS decision in October 2023 using the VQI
Following CMS expansion of TF-CAS coverage, this study found that TCAR and CEA delivered comparable perioperative outcomes in both standard-risk and high-risk patients, while TF-CAS was associated with higher rates of adverse events. The findings support TCAR as a safe alternative to CEA and raise questions about broader adoption of TF-CAS.
August 2022, Journal of Vascular Surgery, George Q. Zhang, MN, MPH
Transcarotid artery revascularization is associated with similar outcomes to carotid endarterectomy regardless of patient risk status
In more than 124,000 carotid procedures, TCAR achieved stroke outcomes comparable to carotid endarterectomy in both standard- and high-risk patients, while transfemoral carotid stenting showed higher stroke risk—supporting TCAR as a distinct and potentially broader treatment option.
Durability
Columbo JA, Martinez-Camblor P, Stone DH, Goodney PP, Creager MA, MacKenzie TA, Chen H, O'Malley AJ, Hicks CW. Three-year risk of stroke after transcarotid artery revascularization versus carotid endarterectomy among Medicare beneficiaries. J Vasc Surg. 2025 Jul 11:S0741-5214(25)01401 6.doi:10.1016/j.jvs.2025.06.052. Online ahead of print.
Long-Term Stroke Outcomes of TCAR vs. CEA
To understand long-term stroke outcomes between TCAR and CEA.
Stroke Rates
| TCAR | CEA | Hazard Ratio | |
|---|---|---|---|
| Asymptomatic | 5.1% | 4.9% | HR = 1.1 |
| Symptomatic | 16.6% (S); 25.4% (D) | 13.6% (S); 21.2% (D) | HR = 1 |
November 2025, Journal of Vascular Surgery, Jesse A. Columbo
Three-year risk of stroke after transcarotid artery revascularization versus carotid endarterectomy among Medicare beneficiaries
Across more than 31,000 carotid intervention, this study demonstrates that TCAR provides durable stroke prevention comparable to CEA through 3 years of follow-up, with no significant difference in long-term stroke risk among either symptomatic or asymptomatic patients. The findings suggest that the benefits of TCAR are maintained beyond the perioperative period, supporting its long-term durability as a carotid revascularization strategy.
Reproducibility
February 2019, Journal of Vascular Surgery, Mathew W. Mell, MD, MS
Variability in hospital costs for carotid artery revascularization
The findings suggest that adopting standardized vascular surgery practice patterns may offer a reproducible strategy for reducing the cost of carotid revascularization.
August 2022, Annals of Surgery, Mahmoud B. Malas, MD, MHS
TransCarotid Revascularization With Dynamic Flow Reversal Versus Carotid Endarterectomy in the Vascular Quality Initiative Surveillance Project
Compared with CEA, TCAR delivered comparable neurologic outcomes through 1 year while reducing myocardial infarction, cranial nerve injury, and other perioperative morbidities, supporting TCAR as a less invasive alternative with similar effectiveness.
January 2020, Journal of the American College of Surgeons, Vikram S. Kashyap, MD, FACS
Learning Curve for Surgeons Adopting Transcarotid Artery Revascularization Based on the Vascular Quality Initiative-Transcarotid Artery Revascularization Surveillance Project
TCAR demonstrated a short and safe learning curve, with stroke and mortality rates remaining low even during a surgeon's first five cases, while procedural efficiency and bleeding outcomes improved with experience.
Patient Compatibilty
January 2022, Journal of Vascular Surgery, Ali F. AbuRahma, MD
The Society for Vascular Surgery implementation document for management of extracranial cerebrovascular disease
The document operationalizes SVS carotid guidelines, offering a standardized approach to patient evaluation, treatment selection, and the use of CEA, TCAR, and TF-CAS to optimize stroke prevention.
February 2022 Journal of Vascular Surgery, Sarah E. Deery, MD, MPH
In-hospital and one-year outcomes are similar for women and men following transcarotid artery revascularization in symptomatic and asymptomatic patients
TCAR provided comparable perioperative and 1-Year stroke/death in women and men following TCAR regardless of symptom status. TCAR appears to be as safe of a surgical procedure for women as for men in patients with both symptomatic and asymptomatic carotid artery disease.
September 2020, Journal of Vascular Surgery, Hanaa Dakour-Aridi, MD
The impact of age on in-hospital outcomes after transcarotid artery revascularization, transfemoral carotid artery stenting, and carotid endarterectomy
Across a broad real-world VQI cohort, TCAR delivered comparably low stroke and mortality event rates across age groups, including elderly patients who have historically been at higher risk with transfemoral carotid stenting.
May 2021, Journal of Vascular Surgery, Christin L. Cui, BS
Effects of timing on in-hospital and one-year outcomes after transcarotid artery revascularization
Urgent TCAR within 48 hours of symptom onset was associated with increased perioperative neurologic risk, whereas TCAR performed 3–14 days after symptoms demonstrated favorable early and 1-year outcomes.
References:
* Lead-in + pivotal phases.
** Pivotal + extended phases.
1. Kwolek CJ, et al. Results of the ROADSTER multicenter trial of transcarotid stenting with dynamic flow reversal. J Vasc Surg. 2015 Nov;62(5):1227–34.
2. Malas MB, et al. Analysis of the ROADSTER pivotal and extended-access cohorts shows excellent 1-year durability of transcarotid stenting with dynamic flow reversal. J Vasc Surg.2019;69(6):1786–1796.
3. Kashyap VS, et al. Early Outcomes in the ROADSTER 2 Study of Transcarotid Artery Revascularization in Patients With Significant Carotid Artery Disease. Stroke. 2020 Sep;51(9):2620–2629.
4. Kashyap, VS. et al. One-year outcomes after transcarotid artery revascularization (TCAR) in the ROADSTER 2 trial. Journal of Vascular Surgery, Volume 76, Issue 2, 466–473.e1.
5. ROADSTER 3 30 Day Follow-up results presented by Meghan Dermody at VIVA 2024.
6. ROADSTER 3 1-Year Follow-up results presented by Meghan Dermody at VIVA 2025.